Two Routes Out of the Same Starting Point
Slide 14 is titled "The Regulatory Landscape & Commercial Viability," and it is the slide in this deck that explains why two techniques that sound similar end up in completely different places commercially. The layout is two parallel tracks diverging from a single point on the left, which the slide labels as the starting point: fat grafting innovation. The upper track is the SVF route; the lower track is the ADSC route. Each track runs through three boxes — classification, reality, trade-off — before arriving at a shared panel of future needs on the right. If you are here looking into body contour services, the sections below walk through the process from the first quote to the finished job.
The short version
- The slide separates the SVF and ADSC routes by how regulators classify each cell preparation, not by which technique is better.
- SVF is classified as minimally manipulated autologous tissue, abbreviated HCT/P, which allows an easier and lower-cost clinical route.
- The SVF route's trade-off is highly variable patient-to-patient yield and a retention gain the slide puts at approximately 17 percent.
- ADSC is classified as an Advanced Therapy Medicinal Product with an IND, governed by strict Good Manufacturing Practice.
- The ADSC route is credited with homogeneous quality and a retention gain of approximately 64.6 percent, at higher cost.
- The slide lists three future needs: standardised potency assays, closed automated systems and mandatory multi-centre long-term registries.
That branching structure is the whole argument of the slide. The two routes do not differ because one is a better technique. They differ because of how each cell preparation is classified by regulators, and the classification determines what is required to offer it, what it costs to produce, and how consistent the output can be. The retention percentages the deck attaches to each route are consequences of that, not independent facts about fat.
The SVF Route: Classification, Reality, Trade-Off
The slide classifies the SVF route as minimally manipulated autologous tissue, which it abbreviates as HCT/P. The reality it describes is an easier, faster path to the clinic with lower costs. The trade-off it lists is highly variable patient-to-patient yield, and lower overall retention gains, which the slide quantifies at approximately 17 percent. Each of those three boxes is a consequence of the first. If the preparation is treated as minimally manipulated tissue taken from and returned to the same person, the regulatory pathway is lighter, and a lighter pathway is what makes a faster and cheaper route possible. The same lightness is why the output is variable: the cell yield depends on the donor, and nothing in the process standardises it.
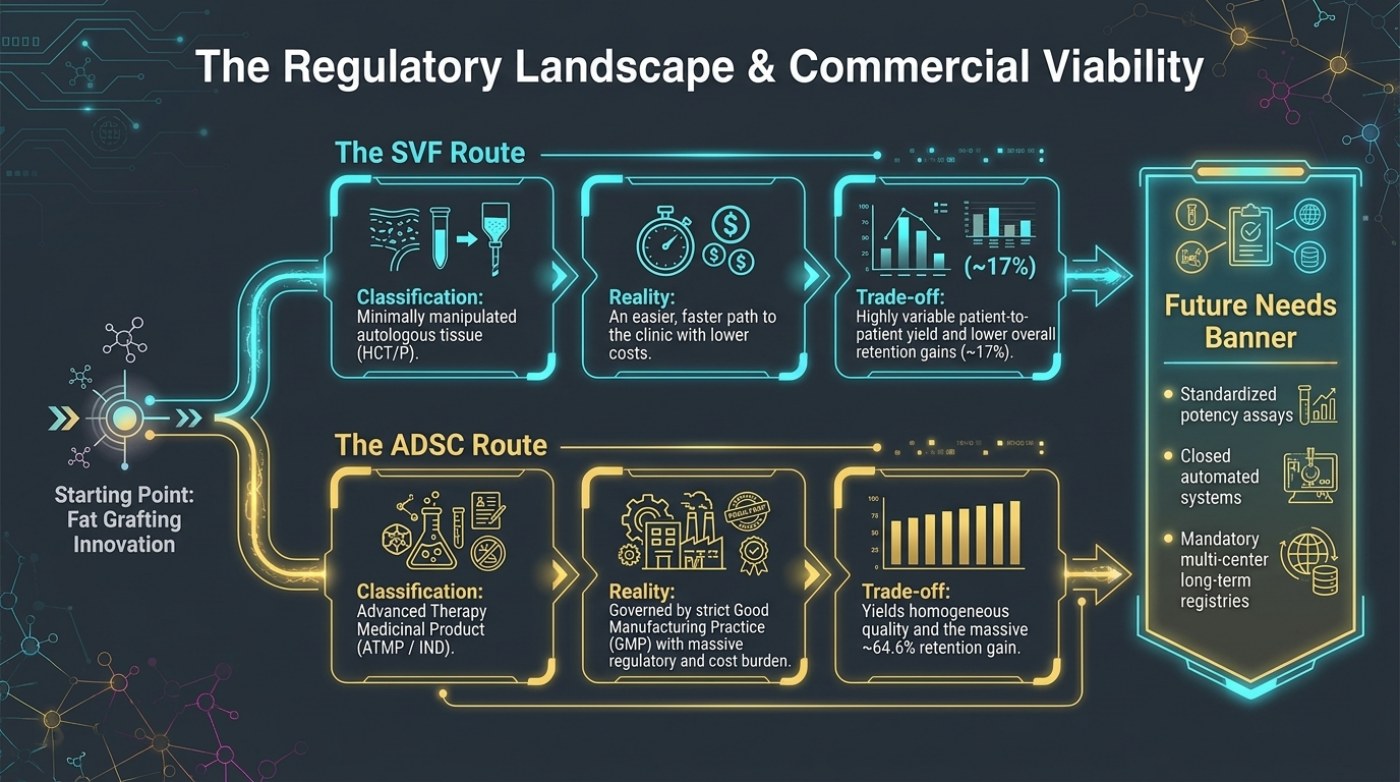
The 17 percent figure is the deck's own, and it is paired on the slide with a chart motif rather than a citation. It should be read as the number this source material attaches to the SVF route's retention gain, not as a figure traceable to a named trial on the slide itself. The direction of the comparison is the point: the lighter regulatory route buys speed and cost and gives up consistency and retention.
The ADSC Route: Classification, Reality, Trade-Off
The lower track classifies the ADSC route as an Advanced Therapy Medicinal Product, abbreviated ATMP, with an IND alongside it. The reality it describes is governance under strict Good Manufacturing Practice, with a massive regulatory and cost burden. The trade-off is stated in the other direction from the SVF track: the ADSC route yields homogeneous quality and what the slide calls the massive retention gain of approximately 64.6 percent.
Again the boxes follow from the classification. Once a preparation is regulated as a medicinal product rather than as minimally manipulated tissue, it has to be produced under a manufacturing standard designed for pharmaceuticals, which brings validated processes, environmental controls and documentation. That is what produces a homogeneous output — the same product every time rather than whatever a given donor yielded — and it is also what produces the cost and the delay. The slide presents the two routes as a genuine trade rather than as one being wrong.
| Element | The SVF route (upper track) | The ADSC route (lower track) |
|---|---|---|
| Classification on the slide | Minimally manipulated autologous tissue (HCT/P) | Advanced Therapy Medicinal Product (ATMP / IND) |
| Reality on the slide | An easier, faster path to the clinic with lower costs | Governed by strict Good Manufacturing Practice (GMP) with massive regulatory and cost burden |
| Trade-off on the slide | Highly variable patient-to-patient yield; lower overall retention gains, approximately 17% | Yields homogeneous quality and a retention gain of approximately 64.6% |
| What the classification drives | A lighter pathway, hence speed and lower cost | A manufacturing-standard pathway, hence consistency and higher cost |
The Retention Figures Side by Side
The two percentages are the most quotable numbers on the slide and the ones most likely to be lifted without their context. The slide attaches each to a route, not to a clinical trial, and it presents them through chart motifs rather than as quoted study results. Presented side by side with their source, they read as the deck's summary of what each route delivers.
| Figure as printed on the slide | Route it belongs to | Attribution | Reading note |
|---|---|---|---|
| Approximately 17% | SVF route | Stated on the regulatory slide as the route's retention gain | Paired with variable patient-to-patient yield in the same box |
| Approximately 64.6% | ADSC route | Stated on the regulatory slide as the route's retention gain | Paired with homogeneous quality in the same box |
| Both figures as a pair | Comparison across routes | Stated together on the same slide | The slide does not compare patient populations, so the two numbers describe routes rather than matched groups |
The two figures also differ in what they describe. The SVF number tracks what a given preparation yielded for the patients in front of whoever was measuring, so a low average with wide scatter is exactly what the slide's phrase about variable patient-to-patient yield describes. The ADSC figure is presented as the output of a controlled process, which only means anything if the process is reproducible, and reproducibility is what the manufacturing standard exists to provide. Neither number comes from a matched comparison of the two routes in the same patients, and the slide does not present one.
What the Slide Says the Field Still Needs
The panel on the right of the slide is titled Future Needs, and it lists three items: standardised potency assays, closed automated systems, and mandatory multi-centre long-term registries. Each addresses one of the gaps the two tracks leave open. A potency assay is what would let a clinician know what a preparation actually contains rather than what was intended. A closed automated system is what would reduce the donor-to-donor variability that the SVF track concedes. Mandatory multi-centre long-term registries are what would generate the kind of longitudinal evidence the previous slide relies on, across a population far larger than any single study.
| Future need on the slide | Gap it addresses | Which route's limitation it targets |
|---|---|---|
| Standardised potency assays | Being able to state what a preparation contains | Both, and most acutely the variable-yield SVF route |
| Closed automated systems | Donor-to-donor and operator-to-operator variability | The SVF route's variable yield |
| Mandatory multi-centre long-term registries | Long-horizon safety and outcome evidence at scale | Both, and the evidence base behind the safety discussion |
Read as a whole, the slide is a description of a field mid-transition. One route is accessible and inconsistent; the other is consistent and expensive; and the three future needs it names are the conditions under which the difference between them would narrow.
Frequently Asked Questions
What is the difference between the SVF and ADSC routes on this slide?
The classification. The slide calls the SVF route minimally manipulated autologous tissue, abbreviated HCT/P, and the ADSC route an Advanced Therapy Medicinal Product, abbreviated ATMP with an IND. The SVF route is described as an easier, faster and lower-cost path, while the ADSC route is governed by strict Good Manufacturing Practice.
What retention figures does the slide give?
Approximately 17 percent for the SVF route and approximately 64.6 percent for the ADSC route. The slide attaches each figure to a route rather than quoting a named trial for it, and it pairs the 17 percent with variable patient-to-patient yield and the 64.6 percent with homogeneous quality.
What future needs does the slide list?
Three: standardised potency assays, closed automated systems, and mandatory multi-centre long-term registries. Each is aimed at a gap the slide has just described — knowing what a preparation contains, reducing donor variability, and generating long-horizon evidence at scale.
This is published information, not medical advice — a board-certified surgeon must assess whether a procedure suits you.
Related Reading
- Why Transplanted Fat Survives — or Does Not
- Verifying Surgeon Credentials and Facility Accreditation
- Liposuction Cost Anatomy: What the Fees Cover
Estimating and comparing your own situation: credentials verifier quote comparison.